A Nigerian nursing final year project’s sample size depends on one decision made before any formula is touched: is your population finite and countable (every nurse currently on staff at one named hospital) or open and effectively unknown (patients presenting with a given condition over an unspecified period)? Get that classification right first, and the formula choice — Taro Yamane for the finite case, Cochran’s formula for the open case — follows automatically.
| Population type | Nursing example | Appropriate approach | Notes |
|---|---|---|---|
| Finite, known population | All nurses currently employed at one named hospital or ward (a countable staff list exists) | Taro Yamane’s formula: n = N / (1 + N(e)²) | Needs an actual N — the hospital’s HR or nursing-services department should be able to confirm current staff numbers |
| Infinite or unknown population | Patients presenting with a given condition at a facility over an unspecified or ongoing period | Cochran’s formula: n = Z²pq / e² | Use p = 0.5 (maximum variability) when no prior study gives you a better estimate of the proportion |
| Small qualitative purposive sample | In-depth interviews with nurse-managers, or a focus group with patients about a specific care experience | Data saturation, not a formula | Typically 6–15 interviews depending on design, justified by when new interviews stop producing new themes, not by a fixed number decided in advance |
A worked example: Taro Yamane for a hospital nursing staff population
Illustrative only — replace with your real facility’s confirmed figure. If a hospital’s nursing department confirms N = 180 nurses, and you accept a 5% margin of error (e = 0.05), Taro Yamane’s formula gives: n = 180 / (1 + 180 × 0.05²) = 180 / (1 + 0.45) = 180 / 1.45 ≈ 124. State the confirmed N, the margin of error you chose and why, and the full substituted calculation in your Chapter Three — not just the final rounded number.
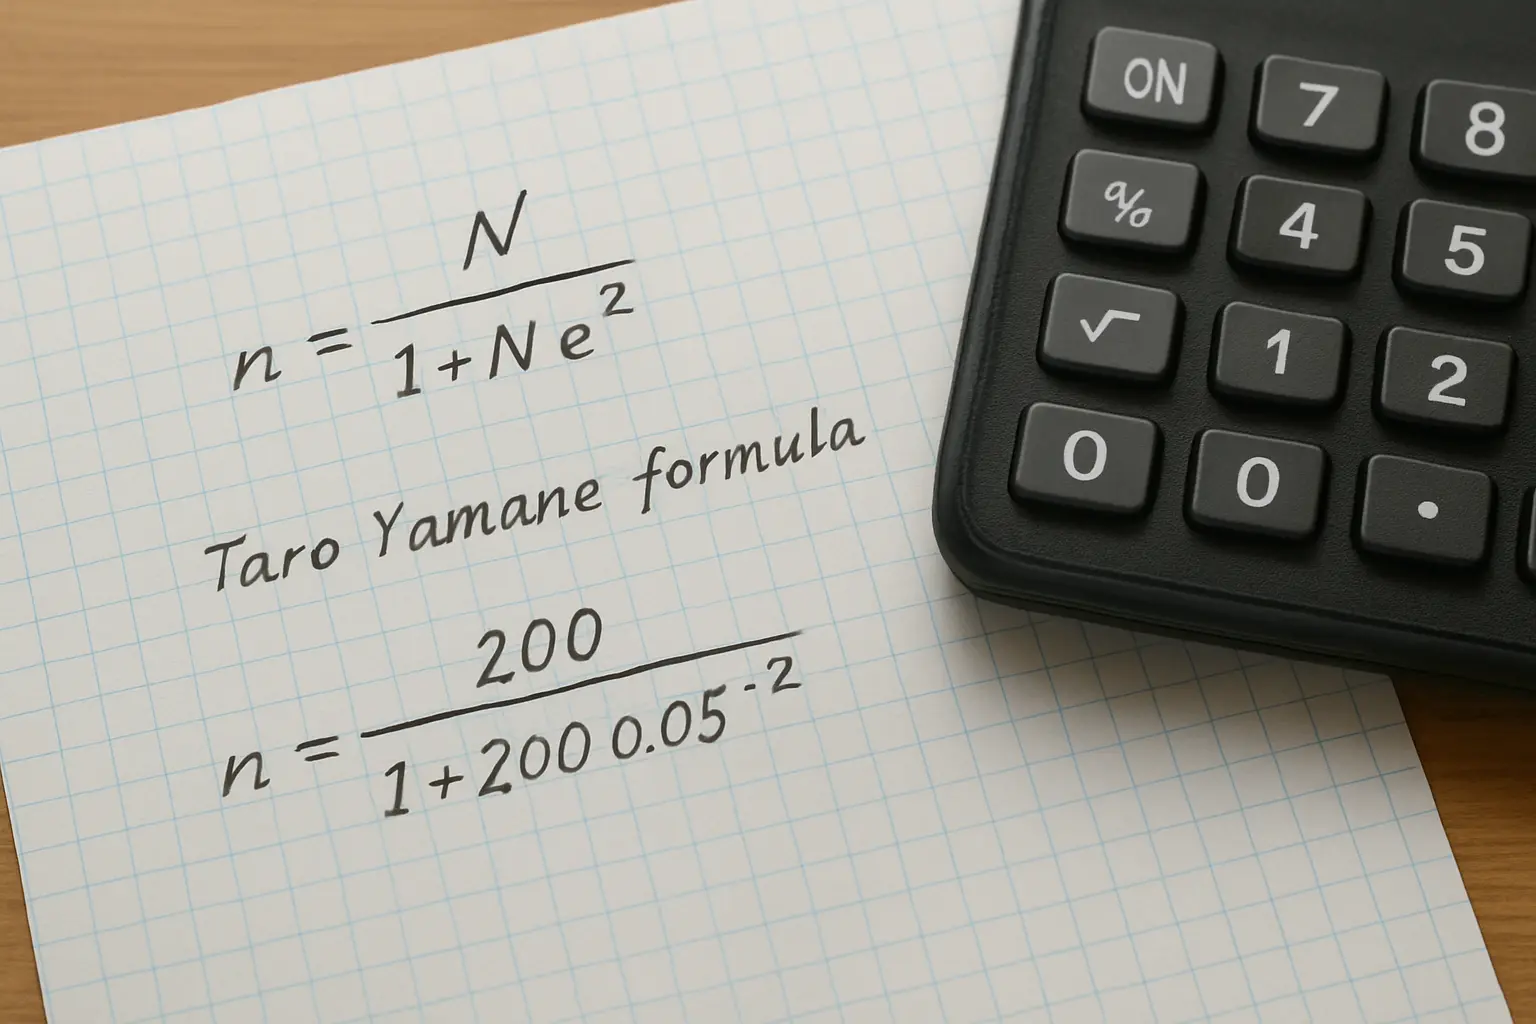
A worked example: Cochran’s formula for an open patient population
Illustrative only. For a 95% confidence level (Z = 1.96), maximum variability (p = q = 0.5), and a 5% margin of error: n = (1.96² × 0.5 × 0.5) / 0.05² = 0.9604 / 0.0025 ≈ 384. This is the standard “unknown population” sample size figure cited across many disciplines at these confidence and error settings — state your own chosen confidence level and margin of error explicitly rather than reusing 384 without checking whether your own assumptions match.
What inclusion and exclusion criteria does a nursing panel expect?
Every nursing project needs an explicit inclusion and exclusion list, stated before data collection, not decided informally as you go. Typical inclusion criteria: confirmed diagnosis or condition matching your study’s focus, a defined age range appropriate to your topic, currently admitted or attending the specific facility during your data-collection window, and capacity to give informed consent. Typical exclusion criteria: patients who are critically ill or otherwise unable to safely participate, those lacking capacity to consent and without an appropriate proxy consent process in place, and anyone outside your defined age range or diagnostic criteria. State both lists explicitly in Chapter Three — a panel checking your methodology will ask how a specific difficult case (a patient who was borderline eligible, for example) was actually handled, and a project with no stated criteria has no defensible answer.

Common sample-size mistakes that get a nursing Chapter Three sent back
Three faults recur often enough to name directly. First, applying Taro Yamane to a population you have not actually confirmed — quoting a hospital’s total staff count from memory or a guess rather than a figure the facility itself confirmed is a sourcing problem the formula cannot fix. Second, changing your margin of error after the fact to hit a sample size you had already decided you wanted — the margin of error should be chosen and justified before you see what number it produces, not adjusted afterward to reach a convenient figure. Third, quoting a formula’s final number without showing the substitution — a panel checking your Chapter Three wants to see 180 divided by 1.45, not just “n = 124” appearing with no working shown.
How does your sample size affect which statistical test you can run later?
Your sample size decision in Chapter Three has direct consequences for Chapter Four — several common statistical tests have minimum sample-size or expected-cell-count assumptions (a chi-square test, for example, generally needs an expected count of at least five in most cells to be valid), and a sample calculated correctly by Taro Yamane or Cochran can still turn out too small once split across the subgroups your analysis actually compares. Think forward to your planned analysis while you are still setting your sample size, not only backward from the formula — if your project will compare several subgroups, either increase your target sample accordingly or choose a test suited to smaller subgroup sizes.
How do you choose a sampling technique, not just a sample size?
The formula gives you a number; a separate decision gives you how you actually select who fills that number. Simple random sampling (drawing names from a full staff or patient list) works well against a finite, fully known population like the hospital-staff example above. Stratified sampling (dividing your population into subgroups — by ward, by shift, by seniority — then sampling proportionally within each) is common where your population is not uniform and you need every subgroup represented. Purposive or convenience sampling is standard for qualitative work and for populations you cannot fully enumerate in advance, but state explicitly why you chose it and what that choice means for how far your findings can generalise. Whichever technique you choose, it should match the population type in the table above — a purposive sample dressed up with a Cochran’s-formula number attached is a mismatch a careful panel will notice.
How does ethics approval interact with your sampling plan?
Your inclusion and exclusion criteria, and how you plan to approach and recruit participants, are usually reviewed as part of your ethics approval process, not decided separately from it — an ethics committee reviewing your application will check that your recruitment plan matches your stated criteria, and any change to your sampling plan after approval generally needs to go back to the committee rather than being made informally in the field. The site’s guide to ethics approval for a nursing project in Nigeria covers what a Health Research Ethics Committee application needs to state about your target population, and reading it alongside this guide means your sampling plan and your ethics application describe the same population consistently — a mismatch between the two documents is a common and entirely avoidable error.
What if your study is qualitative, not survey-based?
Taro Yamane and Cochran’s formula both assume a quantitative, statistically representative sample — they do not apply to a qualitative interview or focus-group study, where sample size is justified by data saturation instead. The site’s fuller guide to how many respondents you need for a qualitative final year project covers that justification in depth, including what the published evidence actually says about typical interview and focus-group counts across disciplines.
How does this compare to sample-size reasoning in another field on this site?
The finite-population Taro Yamane logic used above for a hospital’s nursing staff is the same logic the site’s sample size guide for an agriculture project uses for a farmer population — the formula does not change between fields, only the population you plug into it and how defensibly you can source that population figure. For the fuller Chapter Three structure this section sits inside, see the site’s guide to writing Chapter Three of a Nigerian final year project, and for a fully worked chapter-by-chapter nursing project that shows this section in context, see the site’s complete nursing final year project example.
Where Tesify fits
Tesify can help you draft the Chapter Three prose around your population and sample-size reasoning — the sentences that explain and justify your chosen formula and sampling technique — while the actual population figure, your chosen margin of error, and your inclusion/exclusion criteria have to come from your own study design and your facility’s confirmed numbers. Start with Tesify’s free plan to draft your Chapter Three population and sampling section.
Frequently Asked Questions
What margin of error is standard for a Nigerian nursing final year project?
5% is the most commonly used margin of error in undergraduate nursing projects, though some departments accept up to 10% for a smaller-scale study — confirm your department’s expectation rather than assuming 5% is mandatory.
Can you use Taro Yamane’s formula if you are not certain of your exact population size?
No — Taro Yamane specifically needs a known N; if your population figure is an estimate rather than a confirmed count, either work to confirm the real figure with the facility or treat your population as effectively unknown and use Cochran’s formula instead.
What response or attrition rate should you plan for beyond your calculated sample size?
Many Nigerian nursing projects add 10–20% to their calculated sample size to account for incomplete questionnaires, withdrawals, or non-response — state this inflation explicitly in Chapter Three if you use it, rather than silently over-sampling with no stated reason.
Do you need a different formula for a comparative study between two groups?
A comparative design (comparing two wards, two facilities, or two patient groups) typically needs a sample-size calculation for each group separately, and sometimes a power-analysis approach rather than a simple Taro Yamane or Cochran calculation — consult your supervisor or a statistics resource specific to comparative designs before finalising your number.
Can family members or caregivers count toward your sample instead of the patient directly?
Only if your research question is actually about the caregiver’s own experience or perspective — recruiting a caregiver as a proxy respondent for the patient’s own experience changes what you are actually measuring and should be stated explicitly as a methodological choice, not treated as interchangeable with the patient.
How precisely should your inclusion criteria state an age range?
State exact boundary ages (for example, “18 to 65 years inclusive”) rather than a vague range, and be explicit about which boundary is included — a panel checking your Chapter Four sample description will compare it directly against this stated criterion.
What if the hospital cannot give you an exact staff or patient population figure?
Request the closest official estimate the facility can confirm in writing (even a recent range or a figure as of a stated date), cite it as such with the date it was confirmed, and note the uncertainty explicitly in your limitations section rather than presenting an unconfirmed guess as a precise N.
Does a smaller final sample than calculated automatically invalidate your project?
No, provided you disclose the shortfall honestly, explain the likely reason (refusals, access constraints, time pressure), and discuss what it means for how confidently your findings can be generalised — an honestly reported shortfall is a limitation, not automatic grounds for rejection.